Auditory Scene
At a glance
Middle ear myoclonus is a muscular form of objective tinnitus caused by involuntary contractions of the stapedius or tensor tympani muscle in the middle ear.
Episodes of clicking, fluttering, crackling or buzzing that are not in time with the heartbeat, with a sense of vibration in the ear, are the main symptoms; hearing is usually normal.
It is not an emergency, but accompanying neurological symptoms such as facial weakness, difficulty swallowing or speaking, or unsteadiness should be assessed promptly.
Explanation and reassurance, reducing triggers and tinnitus counselling come first; medication, botulinum toxin and tenotomy are options for the doctor to consider, and the evidence is weak.
Medical disclaimer. This content is for informational purposes only and does not replace a physician’s examination, diagnosis or treatment; it should not be used as medical advice. For your complaints or personal situation, always consult an ear, nose and throat physician and an audiologist.
If clicking, fluttering or buzzing in your ear recurs often or affects your sleep or work, see an ear, nose and throat doctor and an audiologist. Seek prompt neurological assessment if the sound comes with facial twitching or weakness, difficulty swallowing or speaking, double vision or unsteadiness. If the sound beats in time with your heartbeat, tell your doctor specifically; this needs a different assessment.
Definition and epidemiology
Middle ear myoclonus consists of involuntary, rapid, rhythmic or irregular contractions of the two small middle ear muscles, the stapedius and the tensor tympani. The contractions move the ossicular chain and the eardrum, and the patient hears clicking, fluttering, crackling or buzzing. Together with palatal myoclonus, which arises from the palatal muscles, it is described as one of the two muscular causes of tinnitus (Vattoth et al., 2010). Because the sound is mechanical, the examiner can sometimes hear it as well, so it is classed among the causes of objective tinnitus. Objective tinnitus is rare: most tinnitus is subjective, perceived only by the patient, and objective tinnitus may be caused by identifiable conditions such as vascular abnormalities and myoclonus (Tunkel et al., 2014).
Middle ear myoclonus is uncommon and its true frequency is unknown. Tinnitus itself is common, affecting 10-15% of adults, and 25.3% of people in the United States report having experienced it at some time (Tunkel et al., 2014). Myoclonus is a small subgroup within this large population, but it is worth recognising because it calls for its own diagnostic and treatment approach. A systematic review of the literature up to 2011 identified 21 relevant publications, most of them case reports or small case series (Bhimrao et al., 2012). The general features of tinnitus are covered under tinnitus.
Symptoms and signs
The typical complaint is clicking, fluttering, crackling or buzzing in one ear or bilaterally, coming in episodes that last seconds or minutes. The sound is not synchronous with the heartbeat, which distinguishes middle ear myoclonus from pulsatile tinnitus. During an episode the patient may describe fullness, a feeling that the eardrum is fluttering or brief fluctuations in hearing. Symptoms vary through the day; some patients notice that external sounds, stress or facial movements trigger them. Episodes can make it hard to fall asleep or concentrate in quiet surroundings.
Examination is often unremarkable. During an episode, rhythmic movement of the eardrum may be seen on otoscopy, and the sound can sometimes be heard with a stethoscope held near the ear canal. Hearing is usually normal. Rhythmic movement of the soft palate on oral examination suggests that the clicking comes from the palatal muscles rather than the middle ear; this is called palatal tremor (formerly palatal myoclonus). Ear clicking is a common complaint in essential palatal tremor. A review of 103 cases proposed the name ‘isolated palatal tremor’ to reflect the different mechanisms that this group includes (Zadikoff et al., 2006).
Causes and risk factors
In most patients the cause of middle ear myoclonus is unknown and it is regarded as idiopathic. Because the stapedius is supplied by the facial nerve and the tensor tympani by motor fibres of the trigeminal nerve, conditions affecting these nerves or their brainstem nuclei are thought to be able to increase muscle activity. Because most publications are case reports or small series (Bhimrao et al., 2012), however, these links are uncertain and the evidence is limited. Myoclonus has no specific imaging correlate (Vattoth et al., 2010).
Palatal tremor is a separate condition with two forms. In essential palatal tremor the palatal movements are consistent with activity of the tensor veli palatini, the movement stops during sleep and MRI is normal. In symptomatic palatal tremor the levator veli palatini is active, the movement continues during sleep, cerebellar signs are present and MRI shows increased T2 signal in the region of the inferior olive (Deuschl et al., 1994). Because the tensor veli palatini opens the Eustachian tube, its rhythmic contraction opens and closes the tubal orifice and produces clicking in the ear. In isolated palatal tremor, a central generator, peripheral and mechanical causes, voluntary or skill-related movements and psychogenic mechanisms have been described, and these often overlap (Zadikoff et al., 2006). Palatal myoclonus is associated with cerebellar and brainstem disease (Vattoth et al., 2010).
Audiological and clinical assessment
Diagnosis rests mainly on the history, examination and long-time-base tympanometry (Bhimrao et al., 2012). The history covers the character of the sound (clicking or buzzing), its rhythm, any relation to the heartbeat, its duration, triggers and whether it continues during sleep. The audiologist’s main task is to document the source of the rhythmic sound with immittance measurements and to separate it from other causes of objective tinnitus.
- Otoscopy and auscultation: look for movement of the eardrum during an episode, and use a stethoscope to check whether the examiner can also hear the sound.
- Oral and nasopharyngeal examination: rhythmic movement of the soft palate and tubal orifice suggests palatal tremor; check whether the movement is synchronous with the clicking.
- Pure-tone and speech audiometry: usually normal; an accompanying hearing loss calls for investigation of another diagnosis.
- Standard tympanometry: usually type A. Because the trace is recorded in a few seconds, a measurement between episodes may look normal.
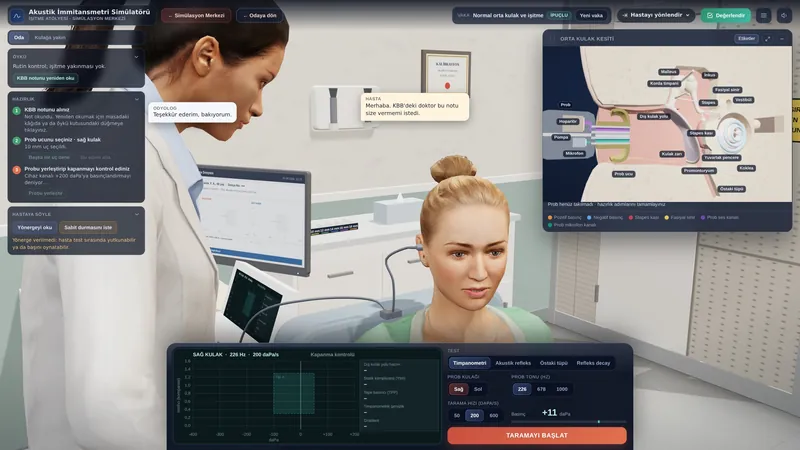
- Long-time-base recording: monitoring compliance for a prolonged period at a fixed pressure or in reflex recording mode shows rhythmic fluctuations that coincide with the contractions, and is the most valuable diagnostic finding (Bhimrao et al., 2012). Matching the trace to the moments when the patient reports the sound strengthens the diagnosis.
- Acoustic reflexes: note the reflex thresholds and whether external sound triggers an episode during recording.
- Imaging: there is no specific finding in middle ear myoclonus (Vattoth et al., 2010); in palatal tremor with neurological signs, MRI of the brainstem and cerebellum may be considered (Deuschl et al., 1994).
| Feature | Middle ear myoclonus | Palatal tremor |
|---|---|---|
| Source | Stapedius or tensor tympani | Tensor or levator veli palatini |
| Sound | Clicking, fluttering, buzzing | Rhythmic clicking |
| Examination | Drum movement during episodes | Rhythmic soft palate movement |
| Immittance | Rhythmic fluctuation on long recording | Changes synchronous with palatal movement |
| Sleep | Variable | Stops in essential, persists in symptomatic |
| Imaging | No specific finding | Olivary T2 signal increase in symptomatic |
The differential diagnosis includes vascular sounds synchronous with the heartbeat, patulous Eustachian tube with breathing-synchronous sound and autophony, palatal tremor and subjective tinnitus. A pulsatile sound points towards vascular causes, and the assessment then follows a different path.
Treatment and audiological rehabilitation
In the systematic review by Bhimrao and colleagues, no diagnostic test or treatment was shown to be conclusively effective; the authors proposed a treatment algorithm based on the available data and clinical experience and stressed the need for high-quality prospective controlled trials (Bhimrao et al., 2012). Treatment is therefore stepped according to the severity of symptoms, and decisions are made together with the doctor. The first step is explanation and reassurance: understanding where the sound comes from and knowing that it is not caused by a dangerous disease markedly reduces distress for many patients. Reducing triggers such as stress, poor sleep and caffeine, tinnitus counselling and sound therapy are used at this stage.
For persistent symptoms, medication such as muscle relaxants or anticonvulsants, botulinum toxin injection and sectioning of the stapedius and tensor tympani tendons through a tympanotomy (tenotomy) have been tried; however, the evidence for these options comes mainly from case reports and small series (Bhimrao et al., 2012). After tenotomy the reflex response of the muscle concerned is lost, so acoustic reflex findings and expectations should be discussed in detail with the patient before surgery. The choice and dose of medication rest with the doctor.
In palatal tremor, treatment depends on the type. In symptomatic palatal tremor, the underlying brainstem or cerebellar lesion is assessed neurologically (Deuschl et al., 1994). Because isolated palatal tremor covers different mechanisms, each case needs individual assessment (Zadikoff et al., 2006). During follow-up, tinnitus questionnaires and repeated immittance recordings help to document the response to treatment.
Impact on quality of life and advice
Recurrent clicking or buzzing in the ear, although usually due to a harmless cause, can lead to anxiety, poor sleep and difficulty concentrating. The fact that others can sometimes hear the sound makes some patients feel embarrassed and avoid social situations. A long wait for a diagnosis, and the impression that the symptom is ‘imagined’, add to the distress; showing the source of the sound with an objective recording can therefore be a considerable relief.
Practical advice: for a few days, note when the sound starts, how long it lasts and what triggers it, and share this with your audiologist; if you can record it on your phone, bring the recording to the appointment. Regular sleep, reducing stress and limiting caffeine may ease symptoms. Using background sound in quiet rooms, such as soft music or nature sounds, makes the clicking less noticeable. If new symptoms appear, such as facial twitching, difficulty swallowing or balance problems, see your doctor without delay.
If you used this review, you can cite it as follows (APA 7):
Auditory Scene. (2026). Middle Ear Myoclonus. Hearing & Balance Health Guide. https://auditoryscene.com/guncel-haberler/categories/isitme-sagligi-rehberi/orta-kulak-miyoklonusu/Permanent link: auditoryscene.com/guncel-haberler/categories/isitme-sagligi-rehberi/orta-kulak-miyoklonusu/ · Last reviewed: October 2026 · License: CC BY-NC-ND 4.0
References
- Bhimrao, S. K., Masterson, L., & Baguley, D. (2012). Systematic review of management strategies for middle ear myoclonus. Otolaryngology-Head and Neck Surgery, 146(5), 698-706.
- Deuschl, G., Toro, C., Valls-Solé, J., et al. (1994). Symptomatic and essential palatal tremor. 1. Clinical, physiological and MRI analysis. Brain, 117(4), 775-788.
- Tunkel, D. E., Bauer, C. A., Sun, G. H., et al. (2014). Clinical practice guideline: Tinnitus. Otolaryngology-Head and Neck Surgery, 151(2_suppl), S1-S40.
- Vattoth, S., Shah, R., & Curé, J. K. (2010). A compartment-based approach for the imaging evaluation of tinnitus. American Journal of Neuroradiology, 31(2), 211-218.
- Zadikoff, C., Lang, A. E., & Klein, C. (2006). The ‘essentials’ of essential palatal tremor: A reappraisal of the nosology. Brain, 129(4), 832-840.
Frequently asked questions
Can other people hear the clicking in my ear?
Sometimes, yes. In middle ear myoclonus the sound is a real, mechanical sound produced by the muscles moving the ossicles and eardrum; it can be heard by someone listening closely or by an examiner with a stethoscope. This is why it is called objective tinnitus.
Is middle ear myoclonus dangerous?
It is usually harmless and does not damage hearing permanently. It can, however, be bothersome and affect sleep. If it comes with other symptoms such as facial twitching, difficulty swallowing or speaking, or unsteadiness, a neurological assessment is needed.
Which tests are used to diagnose it?
In addition to ear examination and a hearing test, movement of the middle ear is recorded for a prolonged period with an immittance meter. The contractions appear as rhythmic fluctuations on this trace. Examining the mouth helps to tell whether the sound comes from the palatal muscles.
Will I need an operation?
Most patients do not. Explanation, reducing triggers and tinnitus counselling are usually the first steps. For severe, persistent symptoms, medication, botulinum toxin or cutting the tendons of the middle ear muscles may be considered; the evidence for these options is limited and the decision is made with your doctor.
The sound in my ear beats with my heart. Is this myoclonus too?
Probably not. A sound in time with the heartbeat is called pulsatile tinnitus and is often due to a vascular cause. Different tests and imaging may be needed, so make sure you tell your doctor about the rhythm of the sound.
I was told my palate is twitching. Is this related to my ear?
Yes. In palatal tremor the muscles of the soft palate contract rhythmically, and the opening and closing of the Eustachian tube can be heard as clicking in the ear. The type of palatal tremor is determined by neurological examination and, if necessary, MRI.
A scale that can be used to assess the impact of clicking and buzzing in the ear on daily life: